Menampilkan postingan yang diurutkan menurut tanggal untuk kueri vitamin d. Urutkan menurut relevansi Tampilkan semua postingan

Fat Soluble Vitamin C Supplement

Fat Soluble Vitamin C Supplement

There's little doubt that vitamin C is of great benefit to the human body. However, how you consume vitamin C makes a huge difference in the amount your body is able to absorb and use (a feature of all supplements called "bioavailability").

Liposomal (or pro-liposomal) vitamin C is a groundbreaking option for high-dose vitamin C.

Between 14-30% of the vitamin C consumed in supplement form is actually absorbed by the body. ( Source 1) That number can vary greatly depending on your own vitamin C needs and the type of supplements you take. Consuming five servings of raw foods high in vitamin C per day, such as berries, kiwi, broccoli and citrus, will provide adequate vitamin C. Adding supplemental vitamin C in the form of ascorbic acid, the equivalent form of vitamin C found naturally in foods, will increase blood levels further, but natural absorption of vitamin C above the intake of about 200 mg decreases sharply with increasing doses by as much as 50%. ( Source 2) This may be because our bodies use certain transporters of vitamin C in the small intestine called Sodium-Dependent Vitamin C Transporters (SVCT -1) which will absorb efficiently only up to a certain point and this absorption is regulated by our bodies depending on the level of vitamin C in plasma (blood). In addition, any excess absorbed vitamin C is destined to be  excreted in urine to maintain a small tight control on plasma concentrations. This is where liposomal vitamin C has an advantage.

Liposomes are phospholipid containing microscopic spheres that carry vitamin C at their core. Their absorption does not depend on vitamin C transporters like SVCT-1 but rather on the direct fusion of the liposome with the small intestinal cells resulting in the direct intracellular release of the vitamin C which eventually  ends up into the blood circulation.

Not only does liposomal vitamin C have a substantially higher absorption rate than conventional vitamin C supplements, but it also comes with its own host of health benefits. This is due to the phospholipids used to surround, or encapsulate, the vitamin C — the very mechanism that allows it to bypass the slow vitamin C transporters present in the gut. In this article, I discuss the definition of liposomes and how to choose the best liposomal supplement and potential side effects.

What are liposomes?

Liposomes are actually similar to cells. The same phospholipids that makeup cell membranes also make up the outer shell of liposomes. The inner and outer walls of the liposome are made up of phospholipids, the most common being phosphatidylcholine, to create a lipid bilayer. A double layer of phospholipids (phospholipid bilayer) creates a sphere around an aqueous (water-containing) component, such as dissolved vitamin C.

Because the liposomes' outer shells imitate our cell membranes, liposomes can "fuse" with certain cells upon contact, delivering the liposome's content to the cell.

This is the scientific advantage of the liposomal delivery system.

Liposomes were discovered in the 1960s. This novel delivery system offers a targeted method to get nutrients into the bloodstream without being destroyed by the digestive enzymes and acid found in the digestive tract and stomach respectively.

What is liposomal vitamin C?

In the case of liposomal vitamin C, these phospholipids encapsulate vitamin C at their core.

As mentioned above, liposomes are thought to fuse with the cells responsible for absorbing nutrients making up the gut lining called enterocytes. Because they bypass the normal mechanism of absorbing vitamin C through slow vitamin C receptors type 1 (sodium-dependent vitamin C receptors SCVT 1), the bioavailability is much higher than standard vitamin C supplements. ( Source 3 )

Taking a liposomal form of vitamin C is much more effective and efficient than traditional methods of vitamin C supplementation in terms of absorption.

5 Benefits of Liposomal Vitamin C

Taking standard vitamin C (ascorbic acid) offers several benefits to the human body. These benefits may be magnified when taking liposomal C.

1. Bioavailability

The best-understood advantage is that liposomal vitamin C has a much higher bioavailability than standard vitamin C.

Bioavailable simply means how well vitamin C absorbs into your system. As we already mentioned liposomal vitamin C supplement allows your small intestine to absorb more of the nutrient than a standard vitamin C supplement.

A 2016 study in 11 human subjects found that vitamin C encapsulated in liposomes increased vitamin C levels in the blood by substantially  compared to an un-encapsulated (non-liposomal) supplement at the same dose (4 grams). ( Source 4 )
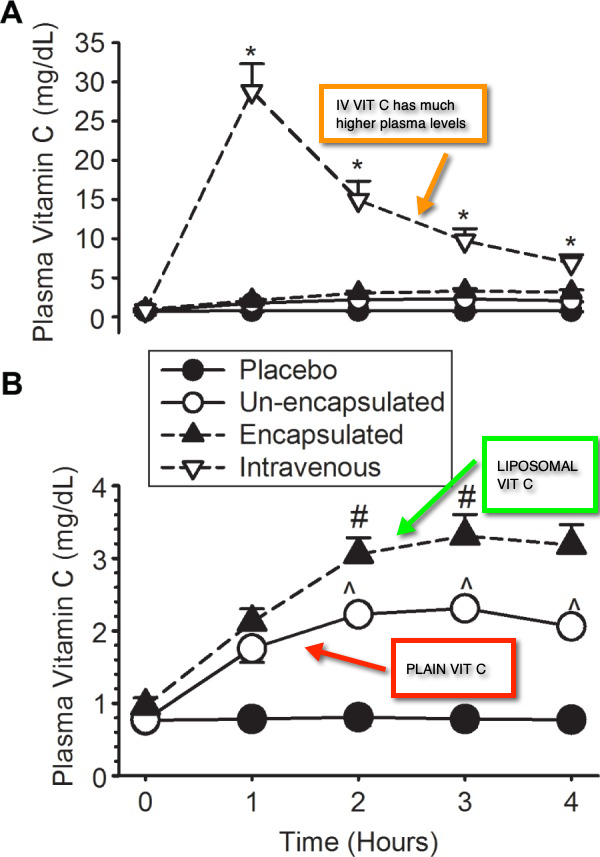
Liposomal vitamin C's bioavailability is only outstripped by intravenous (IV) vitamin C. IV vitamin C which has 100% bioavailability by definition, but is much more invasive, as it requires a needle insertion, a specially trained facility, and 1-3 hours of time for the slow infusion.

High doses of IV vitamin C are used most frequently in conjunction with cancer treatment and provide a pro-oxidant effect which can ONLY be achieved with very high IV doses of vitamin C. The pro-oxidant effect of high dose IV vitamin C is very different than that of low doses of vitamin C which provide anti-oxidant activity.

2. Heart and Brain Health

Vitamin C intake (via diet or supplements) may decrease the risk of cardiovascular disease by about 25%, according to a 2004 analysis published in The American Journal of Clinical Nutrition . ( Source 5 )

Any form of vitamin C supplement improves endothelial function, as well as ejection fraction. ( Source 6 )

Endothelial function involves the contraction and relaxation of blood vessels, enzymatic release to manage blood clotting, immunity, and platelet adhesion. Ejection fraction defines "the percentage of blood that is pumped (or ejected) out of the ventricles" when the heart contracts on every beat.

Together, these results suggest that vitamin C may play an important part in the prevention of cardiovascular disease and the improvement of heart health.

After a stroke or heart attack, it's important to heal the tissues damaged by the lack of oxygen. Once blood flow is restored, the reoxygenation of previously oxygen-deprived cells leads to dtissue damage called "reperfusion injury" which is accompanied by "excessive generation of free radicals". ( Source 7)

When delivered intravenously, vitamin C is a potent antioxidant that can counteract and neutralize free radicals that cause the oxidative stress caused by reperfusion. ( Source 8 )

In one animal study, liposomal vitamin C prevented brain tissue damage from reperfusion when administered before blood flow was restricted. ( Source 9 )

Although blood levels achieved by IV infused vitamin C are much higher than liposomal vitamin C, one study observed that liposomal vitamin C was nearly as effective as IV vitamin C at preventing tissue damage during reperfusion. The research was conducted in 11 subjects who had temporary obstruction of blood flow to their arms blood flow by tourniquet. ( Source 4 )

3. Cancer

Intravenous vitamin C can be used in high doses to fight cancer in tandem with traditional chemotherapy. It may not eradicate cancer on its own, but it can definitely improve the quality of life, increasing energy and mood for many cancer patients.

On a case by case basis, IV vitamin C can even induce regression of cancer. A 2014 review recounts several reports of remission when using IV vitamin C with chemotherapy. ( Source 10 )

However, one should not rely on IV vitamin C to induce remission or treat cancer on it's own, as these cases are isolated at best. Vitamin C can however be a great adjuvant (helper) to traditional cancer treatment.

Liposomal vitamin C has not been specifically tested in human subjects with cancer. Many cancer patients receiving IV vitamin C, however, also use liposomal vitamin C in high doses between IV treatments. After receiving a high dose of IV vitamin C, it is not uncommon for blood levels to drop below normal in the days after the infusion (trough levels). Therefore, it's highly recommended to increase oral intake levels of vitamin C between IV vitamin C infusions especially to prevent low rebound trough plasma levels of vitamin C.

4. Collagen Production

Collagen is the most abundant protein in our bodies, however our own natural collagen production slows around the age of 25. Vitamin C is a cofactor in the enzymes that produce collagen, meaning it is necessary to the function and health of your bones, blood vessels, and joints where collagen abounds. ( Source 11 ). When vitamin C levels run low, such as in times of stress, infection, chronic illness (i.e. diabetes, autoimmune illness which generate high levels of free radicals and oxidative stress), less of it is available for collagen production. Since collagen is the structural protein that holds us together, this can manifest as weaker joints, tendons, blood vessels and connective tissue. More superficially, weaker collagen can manifest as sagging skin with more wrinkles.

5. Oxidative Stress

In general, some level of oxidative stress occurs within every living thing. As a 2006 review puts it:

"There is increasing evidence connecting oxidative stress with a variety of pathological conditions including cancer, cardiovascular diseases, chronic inflammatory disease, post-ischaemic organ injury, diabetes mellitus, xenobiotic/drug toxicity, and rheumatoid arthritis." ( Source 12 )

Vitamin C is a potent antioxidant and is found in generous quantities within the human body. ( Source 13 )

Is liposomal vitamin C truly effective?

There has been a lot of scrutiny of liposomal vitamin C.

One of the most frequently asked questions about liposomal supplements is: Is liposomal vitamin C a "hoax"?

True liposomal or pro-liposomal supplements are non-toxic and can greatly increase your body's ability to absorb the nutrients they incorporate. Because of extensive equipment and technology needed to manufacture them, liposomal supplements tend to be more expensive than conventional vitamin C but they can deliver superior absorption. However there is great variability between products and a little bit of homework and knowledge helps.

How do we know which products are "true" and effective liposomal vitamin C?

As opposed to the term "liposome", the term "liposomal" is unfortunately not well defined. Many products take advantage of this absence of "liposomal" definition.

A "liposome" is a spherical structure made out of a shell formed by phospholipids and surrounded by water.  At the center of a "liposome" is usually a main ingredient, like vitamin C or glutathione, also suspended in water.

"Liposomal" on the other hand does not mean "liposome" — these terms are not one and the same even though they do sound similar. The term liposomal is (sometimes) loosely used to only mean "containing fat". So products containing just fat (lipid) and vitamin C mixed together can sometimes be called "liposomal".

The usual lipid that forms liposomes is a "phospholipid". Phosphatidylcholine is the most abundant phospholipid and is the main building block of cell walls as well as the main constituent of the outer shell of liposomes. However the lipid form that some supplements use is not a phospholipid, and can be simply be in the form of a fatty acid which is not as effective.

Products using fatty acids may be labelled "liposomal" vitamin C but might never result in formed liposomes, even when exposed to water because the vitamin C is simply covalently bound to a fatty acid.

The "Fat Soluble" Vitamin C Ester Myth

A perfect example of a product taking advantage of the "liposomal" term is a type of vitamin C  a  vitamin C ester . Usually labeled as "fat  soluble" vitamin C, esters like Ascorbyl Palmitate are marketed as a "liposomal" but will never result in forming an actual "liposome".

Here are some important facts about "fat soluble" Ascorbyl Palmitate:

  • Ascorbyl palmitate is not found in nature. It is SYNTHETIC, made by combining palmitate (an ester, fat) with vitamin C (Ascorbic Acid).
  • Ascorbyl palmitate is used  as a "FOOD PRESERVATIVE" to extend the shelf life of certain foods, medications, and cosmetics.
  • Ascorbyl Palmitate is also known as "Cetyl Ascorbate"....(two different names for the same compound)
  • Ascorbyl Palmitate is ONLY 42.5% VITAMIN C
  • Products that claim "1600 mg Liposomal Vitamin C" using Ascorbyl Palmitate ONLY PROVIDE 680 mg of actual vitamin C (Ascorbic Acid)

This last point is very important. Because Ascorbyl Palmitate is made by combining vitamin C (Ascorbic Acid) to Palmitate (a fat), less than half of it is true vitamin C ! (source 20, source 21).

Ascorbyl Oleate is another vitamin C ester very similar to the Ascorbyl Palmitate compound, binding Oleate (another fat)  to ascorbic acid.

Ester forms of vitamin C, like Ascorbyl Palmitate, are easily digested after oral ingestion by enzymes in the small intestine which cleave the bond immediately releasing just plain vitamin C (ascorbic acid molecule) and the ester, in this case palmitate, before any absorption can take place.

When this digestion happens, plain vitamin C is released from the ester andno improved absorption occurs when compared to a standard vitamin C supplement. ( source 15, source 16 ). The  bioavailability of fat soluble vitamin C esters is essentially identical to plain vitamin C (Ascorbic Acid) alone. ( Source 18 )

The esters used may even have a negative impact, depending on the ingredient itself.

Unlike natural vitamin C (Ascorbic Acid), Ascorbyl Palmitate may actually be toxic to skin cells damaged by UV exposure according to one study. ( Source 17 )

The bottom line is this: These "Fat Soluble" forms of vitamin C (ascorbyl palmitate, alscorbyl oleate, cetyl ascorbate), are rapidly digested before any absorption takes place, releasing plain vitamin C in your small intestine. Adding to the deception, "Fat Soluble" Vitamin C CONTAINS  LESS THAN HALF actual vitamin C (Ascorbic Acid)!

Unfortunately few people know this, results in unassuming customers paying top dollar for a product that is not much different than a standard vitamin C capsule or powder but has the term "liposomal" attached to it.

Because these forms are inexpensive to make they typically have lower prices, yet they tout very high doses per serving such as 1200-1800 mg of vitamin C.

So, to answer the question: Liposomal vitamin C is not a "hoax", but not all products labeled liposomal vitamin C truly offer the same benefits, especially those selling "Fat Soluble" vitamin C esters.

How to Choose the Best Liposomal Vitamin C Supplement

Several brands offer liposomal vitamin C supplements. Which vitamin liposomal vitamin C supplement is the best?

There are two basic types of liposomal supplements that have to do with "liposome" formation. The first is an already formed liposome vitamin C and, while the other is a pro-liposome. A pro-liposome is chemically bound vitamin C and contains phospholipids in a manner which will result in a liposome formation in the presence of water at body temperature.

The simplest way to tell if a product is a formed liposome is if the ingredients include water. If water is in the ingredients, you are likely dealing with formed liposomes. If not, you are looking at a pro-liposome. Make sure however that both contain phospholipids like phosphatidylcholine (derived from lecithin).

A pro-liposome has the potential to become a liposome when exposed to water, forcing the phospholipids to immediately congregate by natural hydrophobic forces into a bi-layer as described above.

In the form of a pro-liposomal powder, the vitamin C is surrounded (conjugated) by a layer of phospholipids and other fats in a special technical process that can greatly vary in effectiveness. How well this proprietary process of binding the lipids to the vitamin C occurs is key, because if the lipids and the vitamin C are only mixed together (not bound), the formation of liposomes with vitamin C inside will be sporadic at best as the vitamin C can just disperse away separately from the lipids.

Liquid pro-liposomes use lipids (fats) and vitamin C. Based on proprietary manufacturing techniques, these lipids will form liposomes around the main ingredient when they are exposed to water and correct temperature conditions, as are found the environment of the small intestine.

The newly formed liposomes can then be absorbed by the intestinal walls, delivered to and processed by the liver, and released into systemic circulation.

To reiterate: all "liposome" formulations (formed liposomes and pro-liposomes) utilize phospholipids, phosphatidylcholine, lecithin as the fatty agent to form liposomes.

Unfortunately, many vitamin C supplements labeled "liposomal" are, in fact, unable to hold the lipid ingredient and vitamin C together when exposed to water in the small intestine.

Make sure the vitamin C is well-sourced. A good liposomal vitamin C supplement should be non-GMO and preferably use phospholipids derived from sunflower lecithin.

Some customers even insist on knowing that the origin of vitamin C is non-Chinese, but this is a personal preference.

If this is important to you, then look for Quali-C brand vitamin C sourced and made in Scotland from non-GMO European origin corn.

Obviously a  liposomal vitamin C that also offers a satisfaction guarantee with a full refund is a major plus.

To summarize: Avoid the gimmicks and purchase a high-quality liposomal supplement by following these steps:

  1. Choose a formed liposomal or a well made pro-liposomal supplement that contains vitamin C and a phospholipids like phosphatidylcholine. Avoid vitamin C esters "lipid soluble" vitamin C like include ascorbyl palmitate, ascorbyl oleate, or cetyl ascorbate as they may offer little if any advantage over regular vitamin C
  2. Look for the source of vitamin C. While most brand use Chinese vitamin C, Quali-C is a brand of vitamin C manufactured in Scotland using non-GMO European sourced corn
  3. Ensure the supplement is non-GMO and soy-, gluten-, and dairy free.

Dosage of Liposomal Vitamin C

The National Institute of Health advises men and women to never take more than 2,000 milligrams of vitamin C dietary supplement each day.

For specific health issues, a higher dose may be warranted. The Linus Pauling Center recommends a dose of 2,000 milligrams per day, which is generally very safe and can account for the poorer absorption capacity in some individuals. People who may benefit most from this high dose include the elderly and smokers, who also have an increased need for vitamin C.

Generally, 1000-2000 mg/day should afford you the general health benefits of vitamin C:

  • Immunity
  • Brain health
  • Collagen production
  • Cardiovascular protection
  • Energy production
  • Increased antioxidant presence

4,000 milligrams of liposomal vitamin C has been used to protect against the oxidative damage that can happen post-heart attack or stroke due to reperfusion.

While these results are very promising, I suggest stying at around the 2,000 milligram threshold as a daily maintenance dose, unless a healthcare practitioner advises you to take a higher amount, or you have increased levels of oxidative stress from chronic illness or acute infection which require higher doses.

Liposomal Vitamin C Side Effects:

Although a high dose of vitamin C may not technically be "toxic", it may cause side effects like nausea or diarrhea.

Drug Interactions

Vitamin C interacts with certain drugs or nutrients.

ADD and ADHD medications utilize amphetamines. Vitamin C may weaken the effect of amphetamine-based drugs by limiting their effect, although this result has not been reproduced in human subjects. ( Source 19 )

In Summary

  • Liposomal vitamin C is a revolutionary approach to introducing vitamin C into your system.
  • Liposomes use a phospholipid bilayer formed around water and, in this case, vitamin C. The outer casing protects the nutrient inside from damage that might otherwise occur during normal digestion.
  • The absorption of liposomal vitamin C is significantly higher than that of a standard vitamin C supplement.
  • Benefits of liposomal vitamin C include increased bioavailability, cardiovascular support, skin health, improved collagen production, and reduced oxidative stress throughout the body.
  • While many supplements are labeled as "liposomal," some of these use esters of vitamin C (ascorbyl palmitate, ascorbyl oleate, and/or cetyl ascorbate) that do not actually increase the bioavailability of vitamin C and are not going to result in formation of a liposome.
  • Standard doses of vitamin C are between 200-1,000 mg/day.  We recommend 2000 mg per day for most adults.

Sources

  1. Yung, S., Mayersohn, M., & Robinson, J. B. (1982). Ascorbic acid absorption in humans: a comparison among several dosage forms. Journal of pharmaceutical sciences, 71 (3), 282-285. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/7069582
  2. National Institutes of Health: Office of Dietary Supplements. (2018). Vitamin C: Fact Sheet for Health Professionals. Retrieved from: https://ods.od.nih.gov/factsheets/VitaminC-HealthProfessional/
  3. Rivas, C. I., Zuniga, F. A., Salas-Burgos, A., Mardones, L., Ormazabal, V., & Vera, J. C. (2008). Vitamin C transporters. Journal of physiology and biochemistry, 64 (4), 357-375. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/19391462
  4. Davis, J. L., Paris, H. L., Beals, J. W., Binns, S. E., Giordano, G. R., Scalzo, R. L., ... & Bell, C. (2016). Liposomal-encapsulated ascorbic acid: Influence on vitamin C bioavailability and capacity to protect against ischemia–reperfusion injury. Nutrition and metabolic insights , 9 , NMI-S39764. Full text: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4915787/
  5. Knekt, P., Ritz, J., Pereira, M. A., O'Reilly, E. J., Augustsson, K., Fraser, G. E., ... & Pietinen, P. (2004). Antioxidant vitamins and coronary heart disease risk: a pooled analysis of 9 cohorts. The American journal of clinical nutrition , 80 (6), 1508-1520. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/15585762
  6. Ashor, A. W., Lara, J., Mathers, J. C., & Siervo, M. (2014). Effect of vitamin C on endothelial function in health and disease: a systematic review and meta-analysis of randomised controlled trials. Atherosclerosis , 235 (1), 9-20. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/24792921
  7. Nour, M., Scalzo, F., & Liebeskind, D. S. (2012). Ischemia-reperfusion injury in stroke. Interventional neurology , 1 (3-4), 185-199. Full text: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4031777/
  8. Spoelstra-de Man, A. M., Elbers, P. W., & Oudemans-van Straaten, H. M. (2018). Making sense of early high-dose intravenous vitamin C in ischemia/reperfusion injury. Critical Care, 22 (1), 70. Full text: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5861638/
  9. Sinha, J., Das, N., & Basu, M. K. (2001). Liposomal antioxidants in combating ischemia-reperfusion injury in rat brain. Biomedicine & pharmacotherapy , 55 (5), 264-271. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/11428552
  10. Fritz, H., Flower, G., Weeks, L., Cooley, K., Callachan, M., McGowan, J., ... & Seely, D. (2014). Intravenous vitamin C and cancer: a systematic review. Integrative cancer therapies , 13 (4), 280-300. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/24867961
  11. Pullar, J., Carr, A., & Vissers, M. (2017). The roles of vitamin C in skin health. Nutrients , 9 (8), 866. Full text: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5579659/
  12. Suntres, Z. E., & Omri, A. (2006). The role of liposomal antioxidants in oxidative stress. In Nanocarrier Technologies (pp. 191-205). Springer, Dordrecht. Full text:
  13. Figueroa-Méndez, R., & Rivas-Arancibia, S. (2015). Vitamin C in health and disease: its role in the metabolism of cells and redox state in the brain. Frontiers in physiology , 6 , 397. Full text: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4688356/
  14. Meves, A., Stock, S. N., Beyerle, A., Pittelkow, M. R., & Peus, D. (2002). Vitamin C derivative ascorbyl palmitate promotes ultraviolet-B-induced lipid peroxidation and cytotoxicity in keratinocytes. Journal of investigative dermatology, 119 (5), 1103-1108. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/12445199
  15. Dr. Weil: Time for a change? https://www.drweil.com/vitamins-supplements-herbs/vitamins/vitamin-c-time-for-a-change/
  16. The Linus Pauling Institute: The Bioavailability of Different Forms of Vitamin C: https://lpi.oregonstate.edu/mic/vitamins/vitamin-C/supplemental-forms
  17. De Ritter, E., Cohen, N., & Rubin, S. H. (1951). Physiological availability of dehydro-L-ascorbic acid and palmitoyl-L-ascorbic acid. Science, 113 (2944), 628-631. Abstract: https://www.cabdirect.org/cabdirect/abstract/19511402702
  18. Cadeau, C., Fournier, A., Mesrine, S., Clavel-Chapelon, F., Fagherazzi, G., & Boutron-Ruault, M.C. (2016). Vitamin C supplement intake and postmenopausal breast cancer risk: interaction with dietary vitamin C. American Journal of Clinical Nutrition , 104 (1), 228-234. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/27194303
  19. Kiely, M.E., Lal, S., & Nair, N.P. (1987). Effect of ascorbic acid on brain amphetamine concentrations in the rat. Progress in neuro-psychopharmacology & biological psychiatry, 11 (2-3), 287-290. Abstract: https://www.ncbi.nlm.nih.gov/pubmed/3628833
  20. Cambridge Commodities - What is the Percentage of Vitamin C in Ascorbyl Palmitate?   https://www.cambridgecommodities.com/ingredients/ingredient-view,ascorbyl-palmitate_2091.htm
  21. PubChem - Ascorbyl Palmitate - https://pubchem.ncbi.nlm.nih.gov/compound/Ascorbyl-palmitate

Fat Soluble Vitamin C Supplement

Source: https://coremedscience.com/blogs/wellness/how-to-pick-the-best-liposomal-vitamin-c

Share:

Blackmores Vitamin C 1000 Echinacea Zinc Effervescent

Blackmores Vitamin C 1000 Echinacea Zinc Effervescent

Researchers in the United Kingdom say a study on eyesight shows diet and environmental factors are more important than genetics in lowering risk of cataracts.

Eating an apple a day may keep the doctor away, but eating oranges might do the same for cataracts.

In a study published today in the journal Ophthalmology, researchers in the United Kingdom said a higher dietary intake of vitamin C might significantly reduce the risk of developing cataracts.

The study, led by scientists at King's College London, is the first to conclude that dietary and environmental factors play a larger role than genetics in the development of cataracts.

"The findings of this study could have significant impact, particularly for the aging population globally by suggesting that simple dietary changes such as increased intake of fruits and vegetables as part of a healthier diet could help protect them from cataracts," Dr. Chris Hammond, professor of ophthalmology at King's College, consultant eye surgeon and lead author of the study, said in a statement.

Read More: What Is a Cataract? »

The researchers estimated genetic factors account for 35 percent of the difference in cataract progression. Environment and lifestyle account for 65 percent.

To study the impact diet has on cataracts, the researchers tracked the progression of the eye condition in 324 pairs of female twins from the United Kingdom.

The scientists examined digital images of the women's eye lenses when they were about 60 years old. They then studied the same type of images 10 years later.

They kept track of the women's intake of vitamins A, B, C, D, and E. They also tracked their intake of copper, manganese, and zinc using a food questionnaire.

The researchers said the women who ingested more vitamin C initially had a 20 percent reduced risk of developing cataracts. After 10 years, that risk had decreased by 33 percent.

The researchers noted that there was little risk reduction in the women who took vitamin supplements. Instead the preventative effects appeared to be obtained only by eating foods rich in vitamin C.

Dr. Ravi D. Goel, an ophthalmologist from New Jersey who is also a clinical instructor at Wills Eye Hospital in Pennsylvania, said the study provides helpful information for patients and doctors.

"These are novel findings for patients going forward," Goel, a spokesperson for the American Academy of Ophthalmology, told Healthline. "This is a helpful tool for patient education."

Read More: Americans Spend Billions on Vitamins and Supplements That Don't Work »

Cataracts occur when the lens of the eye becomes cloudy due to oxidation over a long period of time.

The researchers said the fluids that bathe the eye are rich in vitamin C, which helps stop the lens from oxidizing.

The dietary intake of vitamin C helps prevent cataracts by increasing the amount of this vitamin in the eye fluid.

The researchers added that smoking and diabetes also are risk factors for certain kinds of cataracts, so a balanced diet and healthy lifestyle are important.

"Healthy diets are always an advantage for patients," added Goel.

Goel also said vitamin C has already been shown to help slow the progression of age-related macular degeneration.

This latest information on cataracts adds to vitamin C's attributes. "It helps overall eye health," he said.

The researchers did note that their observational study has its limitations as it only involved women who were aged 60 years and older.

However, the researchers believe the information could also be relevant for male patients.

Cataracts are the leading cause of blindness in the world, affecting about 20 million people, according to statistics from the World Health Organization (WHO). Cataracts also affect 24 million Americans over the age of 40.

The condition can cause blurry vision, glare, poor night vision, and sensitivity to light.

Initially, better lighting and glasses may help ease some of the symptoms, but as cataracts progress surgery is sometimes needed.

Read More: Diabetes and Blurry Vision: What You Need to Know »

Blackmores Vitamin C 1000 Echinacea Zinc Effervescent

Source: https://www.healthline.com/health-news/vitamin-c-may-reduce-risk-of-cataracts

Share:

Vitamin C For Epilepsy

Vitamin C For Epilepsy

Epilepsy Res. Author manuscript; available in PMC 2016 Feb 1.

Published in final edited form as:

PMCID: PMC4306812

NIHMSID: NIHMS645521

Low brain ascorbic acid increases susceptibility to seizures in mouse models of decreased brain ascorbic acid transport and Alzheimer's disease

Timothy A Warner

aDepartment of Neurology, Vanderbilt University Medical Center, Nashville, Tennessee, 37232, USA

Jing-Qiong Kang

aDepartment of Neurology, Vanderbilt University Medical Center, Nashville, Tennessee, 37232, USA

John A Kennard

bDivision of Diabetes, Endocrinology & Metabolism, Department of Medicine, Vanderbilt University Medical Center, Nashville, Tennessee, 37232, USA

Fiona E Harrison

bDivision of Diabetes, Endocrinology & Metabolism, Department of Medicine, Vanderbilt University Medical Center, Nashville, Tennessee, 37232, USA

Abstract

Seizures are a known co-occurring symptom of Alzheimer's disease, and they can accelerate cognitive and neuropathological dysfunction. Sub-optimal vitamin C (ascorbic acid) deficiency, that is low levels that do not lead the sufferer to present with clinical signs of scurvy (e.g. lethargy, hemorrhage, hyperkeratosis), are easily obtainable with insufficient dietary intake, and may contribute to the oxidative stress environment of both Alzheimer's disease and epilepsy. The purpose of this study was to test whether mice that have diminished brain ascorbic acid in addition to carrying human Alzheimer's disease mutations in the amyloid precursor protein (APP) and presenilin 1 (PSEN1) genes, had altered electrical activity in the brain (electroencephalography; EEG), and were more susceptible to pharmacologically-induced seizures. Brain ascorbic acid was decreased in APP/PSEN1 mice by crossing them with sodium vitamin C transporter 2 (SVCT2) heterozygous knockout mice. These mice have an approximately 30% decrease in brain ascorbic acid due to lower levels of SVCT2 that supplies the brain with ASC. SVCT2+/−APP/PSEN1 mice had decreased ascorbic acid and increased oxidative stress in brain, increased mortality, faster seizure onset latency following treatment with kainic acid (10 mg/kg i.p.), and more ictal events following pentylenetetrazol (50 mg/kg i.p.) treatment. Furthermore, we report the entirely novel phenomenon that ascorbic acid deficiency alone increased the severity of kainic acid- and pentylenetetrazol-induced seizures. These data suggest that avoiding ascorbic acid deficiency may be particularly important in populations at increased risk for epilepsy and seizures, such as Alzheimer's disease.

Keywords: Alzheimer's disease, mouse model, Vitamin C, Electroencephalography, Kainic acid, Pentylenetetrazol

1. Introduction

Seizures are a co-occurring adverse event in Alzheimer's disease (AD), related to amyloid precursor protein (APP) and presenilin 1 (PSEN1) mutations in familial AD, but also affecting many sporadic AD cases, with estimates of prevalence of up to 64 % (Friedman et al., 2012). Non-convulsive seizures (e.g. absence or partial seizures) are harder to distinguish from other abnormal behaviors (Pandis and Scarmeas, 2012) and may be under-reported in AD, particularly by non-medical caregivers.

Ascorbic acid (ASC, vitamin C) is a critical antioxidant in the brain. ASC levels are depleted or deficient in up to 30% of Western populations, particularly in the elderly and hospitalized (Harrison, 2012). ASC is carefully controlled in the brain parenchyma via the sodium dependent vitamin C transporter, SVCT2, which transfers ASC at the choroid plexus from blood into cerebral spinal fluid, and also from extracellular fluid into neurons. This two-step transport process allows accumulation in the brain to far exceed that in blood, except under conditions of prolonged insufficient intake.

Pre- and post-seizure treatments with exogenous ASC moderate the severity of seizures and resultant neurological damage in rodent models (Dong et al., 2013; Gonzalez-Ramirez et al., 2010; Naseer et al., 2011; Santos et al., 2009; Xavier et al., 2007), but ASC deficiency, the more common state in humans, has not been investigated in epilepsy. The objective of this study was to demonstrate whether chronic ASC deficiency increased seizure susceptibility and severity in a mouse model of AD by measuring mortality, behavioral response, and electroencephalography (EEG) responses to pharmacologically-induced seizures, targeting two neurotransmitter systems, GABAergic and glutamatergic.

2. Methods

2.1 Animals

Heterozygous SVCT2 knockout mice (SVCT2+/−; Sotiriou et al., 2002) were crossed with a bigenic mouse carrying two mutations known to cause familial (early-onset) AD (APPSWE/PSEN1dE9; Jackson Laboratories, stock #005864; Fig. 1A). Mice aged 12 to 18 weeks, were maintained in a temperature and humidity controlled environment with ad libitum access to food and water. These mice can synthesize ASC and received no additional supplementation. All procedures were approved by the Institutional Animal Care and Use Committee and were conducted in accordance with the NIH Guide for the Care and Use of Laboratory Animals. All experiments were run, and data analyzed, with the experimenter blinded to genotype.

An external file that holds a picture, illustration, etc.  Object name is nihms645521f1.jpg

Unexplained deaths and increased seizure susceptibility in SVCT2+/− APP/PSEN1 mice

(A) Breeding scheme, genotype and phenotype for experimental mice. (B) Modified Racine scale used for behavioral scoring of seizures. Humane endpoint for euthanization was stage 6, tonic clonic seizures, for 2 consecutive minutes. (C) Increased mortality in SVCT2+/−APP/PSEN1 mice reported as percent deaths from unexplained causes in the colony. Data are for all litters bred in the in-house colony over the past 4 years that reached 6-months of age, and were not removed for other experiments. Total numbers of mice considered given above their respective bars. Data analyzed by Chi2 difference from expected value +++p<0.001. (D) SVCT2+/−, APP/PSEN1 and SVCT2+/−APP/PSEN1 mice have shorter latency to onset of seizure stage 3 following treatment with 10 mg/kg KA (i.p.) in n=6–8 females per genotype. Data were analyzed by 2(APP/PSEN1 genotype) X 2(SVCT2 genotype) ANOVA. *p<0.05, different from wild-type following Bonferroni post hoc comparisons. Mean +Std. Dev. shown.

2.2 Kainic acid (KA) seizure induction

Seizure induction was performed in female mice (n=28) by administration of KA 10 mg/kg, i.p. (Sigma-Aldrich, St. Louis, MO). Seizure-related activity was scored according to a modified Racine scale (Fig. 1B).

2.3 EEG headmount affixation surgery, recording and analysis

Male mice (n=24), were fitted with a prefabricated headmount (Pinnacle Technology Inc.) comprised of three channels; 2 EEG to assess the electrical impulses of the brain, and 1 EMG (electromyography) to measure the muscular activity evoked in the nuchal muscles. Two mice died following surgeries (wild-type and SVCT2+/−APP/PSEN1). Following a 1-week recovery period, synchronized video-EEG/EMG recordings were conducted to assess baseline activity over a 24-h period, quantified in uniform 5-min segments each hour (Arain et al., 2012). Each mouse was then injected with a single dose of the GABAA receptor antagonist, pentylenetetrazol (PTZ; Sigma-Aldrich, St. Louis, MO) 50 mg/kg, i.p. to induce seizure-related activity and monitored during the first 15 min after administration (Binder et al., 2004; Rauca et al., 1999).

A trained observer assessed the spike-and-wave discharges (SWDs) including specific seizure-related events (absence seizures, myoclonic jerks) following previously determined guidelines (Akman et al., 2010; Chung et al., 2009; Snead et al., 1999). SWDs associated with absence seizures and myoclonic jerks were correlated with the appropriate behavioral manifestations in the accompanying video of the EEG/EMG recordings. Abnormal discharges (absence seizure-like activity) and spike discharges (myoclonic jerk-like activity) were quantified regardless of a detectable associated behavior with specific seizure-related events.

2.4 Ascorbic acid and malondialdehyde (MDA)

ASC was measured by an ion pair HPLC and electrochemical detection as previously described (Harrison et al., 2008). MDA was measured as thiobarbituric reactive substances as previously described (Harrison et al., 2010).

2.5 Statistics

Data were analyzed using GraphPad Prism version 5.0 for Mac. KA-seizure induction data, ASC, MDA and EEG data were analyzed using a 2(SVCT2 genotype) X 2(APP/PSEN1 genotype) Univariate ANOVA with Bonferroni post hoc comparisons following significant interactions. Mortality data were analyzed using a Chi2 test against expected mortality.

3. Results and Discussion

3.1 Mortality

There was a startling increase in unexplained deaths prior to 6 months of age in the SVCT2+/−APP/PSEN1 mice (32% of mice) compared to the other three genotypes (8–10% of mice; Fig. 1C). SVCT2+/−APP/PSEN1 mice were observed undergoing seizure-like behaviors in the home cage. Seizures are also a known complication of APP and PSEN1 mutations and are the likely cause of death in these mice. Increased mortality was previously noted in APP/PSEN1 mice that were unable to synthesize ASC due to inactivation of the gulo gene for ASC synthesis and which had been maintained on low ASC supplementation (Harrison et al., 2010), supporting the hypothesis that low ASC contributes to increased mortality through sudden, unexplained deaths in this mouse model of AD.

3.2 KA-induced seizures

In order to pursue seizures as a potential cause of death, we treated mice with KA which causes seizures through glutamate excitotoxicity. SVCT2+/−, APP/PSEN1 and SVCT2+/−APP/PSEN1 mice progressed to stage 3 (repetitive movements) much more quickly than wild-type mice (Fig. 1D; APP/PSEN1: F1,24=27.02, p<0.01; SVCT2+/−: F1,24=14.31, p<0.05). SVCT2+/−APP/PSEN1 mice were the only genotype observed to progress past stage 3, to die or require euthanization (n=2) according to humane endpoints following severe tonic-clonic seizures.

3.3 EEG activity

We next hypothesized that such a severe phenotype would manifest itself as aberrant neural electrical activity, and undertook EEG measurements on 4–6 mice per genotype. Under baseline conditions, there was a trend toward increased incidence of absence seizures and myoclonic jerks in SVCT2+/−APP/PSEN1 mice, although in neither case were differences significant (Fs<2.12, ps>0.16; Fig. 2A, B). Abnormal discharges and spike discharges were not appreciably different in any of the genotypes.

An external file that holds a picture, illustration, etc.  Object name is nihms645521f2.jpg

Seizure-related phenotype expressed in APP/PSEN1 and SVCT2+/−APP/PSEN1 mice in response to PTZ

(A) Occurrence of absence seizures and (B) myoclonic jerks were slightly, but not significantly, increased in SVCT2+/−APP/PSEN1 mice under baseline conditions. EEG recordings were analyzed for the first 15-minutes following administration of 50 mg/kg PTZ (i.p.). (C) Abnormal discharges varied among the groups but not significantly so. (D) Number of myoclonic jerks was greater in mice that were heterozygous for SVCT2. (E) Number of spike discharges, which represent myoclonic jerk-like activity without an associated behavior, was also increased in SVCT2+/− and SVCT2+/−APP/PSEN1 mice. (F) The latency to the first observation of a spike discharge was also significantly shorter in APP/PSEN1, SVCT2+/− and SVCT2+/−APP/PSEN1 mice. (G) Cortex ascorbic acid levels were significantly decreased in SVCT2+/− and SVCT2+/−APP/PSEN1 mice. (H) Lipid peroxidation measured by MDA was significantly elevated in SVCT2+/− and SVCT2+/−APP/PSEN1 mice. A sample EEG/EMG readout for (I) a myoclonic jerk and (J) spike discharge. The EEG recording data are from 4 WT, 5 APP/PSEN1, 6 SVCT2+/−, and 5 SVCT2+/−APP/PSEN1 mice. The ASC and MDA determination data are from 10 WT, 9 APP/PSEN1, 8 SVCT2+/−, and 7 SVCT2+/−APP/PSEN1 mice. All mice were males. *p<0.05, **p<0.01 different from wild-type following Bonferroni post hoc comparisons. Bars show mean ±SEM.

Given these suggestive, but inconclusive data, we determined whether increased seizure susceptibility would also be apparent following seizure induction with PTZ. Following PTZ administration, abnormal EEG discharges (SWDs without an associated behavior arrest) were 3 to 6-fold higher in mutant genotypes compared to wild-types although this was not significant (Fs<2.29, ps>0.15, Fig. 2C). Significantly more myoclonic jerks were observed in SVCT2+/−APP/PSEN1 mice compared to other genotypes (SVCT2 F1,16=15.67, p<0.05; interaction F1,16=31.5, p<0.01; Fig. 2D; I). Spike discharges were also more common in mice heterozygous for SVCT2+/− (F1,16=30.28, p<0.05, Fig. 2E, J). The greatest number was observed in SVCT2+/− APP/PSEN1 mice, driving a trend toward an additional main effect of APP/PSEN1 genotype (F1,16=13.56, p=0.07). The latency to first spike discharge was significantly shorter in all three mutant genotypes compared to wild-types (Fs>10.24, ps<0.01, Fig. 2F). These data suggest that mice of SVCT2+/− and APP/PSEN1 genotypes have aberrant electrical activity that may lower their seizure threshold.

3.4 ASC and oxidative stress

Additional mice (n=14) were treated with PTZ but not assessed with EEG for inclusion in biochemical assays. SVCT2+/− and SVCT2+/−APP/PSEN1 mice had significantly decreased brain ASC, approximately 30% lower than wild-types (F1,30=63.19, p<0.001, Fig. 2G), which was in line with previous reports of these mice (Sotiriou et al., 2002). SVCT2+/− and SVCT2+/−APP/PSEN1 also had increased MDA, which was used as a marker of lipid peroxidation (F1,30=13.82, p<0.05, Fig. 2H).

Given these findings, we hypothesize that oxidative stress contributed to the differences reported in these mice and ASC plays a major role as an antioxidant in cells or at the synapse during seizures. Previous data showed that ASC (250–500 mg/kg i.p.) decreased seizure severity and increased latency to onset following administration of KA, pilocarpine and PTZ. ASC also attenuated oxidative stress during and after active seizure phase and attenuated hippocampal neuronal loss and markers of apoptosis (e.g. caspase-3) and autophagy (Dong et al., 2013; Gonzalez-Ramirez et al., 2010; Naseer et al., 2011; Santos et al., 2009; Xavier et al., 2007). Nevertheless, given the clear data with both KA (kainate receptor agonist) and PTZ (GABAA antagonist) it is likely that ASC also interacts with these neurotransmitter systems in some way. Multiple methods indicate disrupted glutamate transport in human AD postmortem samples (Proper et al., 2002) and mouse models of AD (Minkeviciene et al., 2008).

4. Conclusions

Previous work in this area has been undertaken in wild-type rodents which synthesize their own ASC and have normal ASC transport, and without consideration of the additional sensitivity found in AD. This is the first report where decreased brain ASC, at clinically-relevant levels, impacts seizure susceptibility in both wild-type and APP/PSEN1 mice. We therefore suggest that models of altered brain ASC (such as the SVCT2+/− line used here or the gulo−/− line that, like humans, cannot synthesize ASC) may be particularly useful, and more relevant to animal-based research into seizure-related mechanisms. The most surprising and important finding from this study was that ASC deficiency alone impacted seizure activity. Cognitive decline is accelerated by 5–7 years in AD patients with concomitant epilepsy (Vossel et al., 2013). It is, therefore, possible that preventing deficiency could be a cost-effective and simple way to diminish the occurrence or severity of seizures in some at-risk populations.

HIGHLIGHTS

  • Ascorbic acid deficiency shortened latency to onset of kainic acid-induced seizures

  • APP/PSEN1 mutations shortened latency to onset of kainic acid-induced seizures

  • SVCT2+/−APP/PSEN1 mice have abnormal EEG response to pentylenetetrazol

Acknowledgments

This work was supported by NIH grants AG038739 to FEH and NINDS R01 NS082635 to JQK. The authors would like to thank Zhong Liu for his excellent assistance with mouse headmount affixation surgery and EEG recordings, and Lisa Moore and Shilpy Dixit for assistance with behavioral and biochemical analyses.

Abbreviations

ASC ascorbic acid
AD Alzheimer's disease
APP amyloid precursor protein
EEG electroencephalography
EMG electromyography
KA kainic acid
MDA malondialdehyde
PSEN1 presenilin 1
PTZ pentylenetetrazol
SVCT2 sodium dependent vitamin C transporter

Footnotes

The authors have no conflicts of interest to report.

Publisher's Disclaimer: This is a PDF file of an unedited manuscript that has been accepted for publication. As a service to our customers we are providing this early version of the manuscript. The manuscript will undergo copyediting, typesetting, and review of the resulting proof before it is published in its final citable form. Please note that during the production process errors may be discovered which could affect the content, and all legal disclaimers that apply to the journal pertain.

References

1. Akman O, Demiralp T, Ates N, Onat FY. Electroencephalographic differences between WAG/Rij and GAERS rat models of absence epilepsy. Epilepsy research. 2010;89:185–93. [PubMed] [Google Scholar]

2. Arain FM, Boyd KL, Gallagher MJ. Decreased viability and absence-like epilepsy in mice lacking or deficient in the GABAA receptor alpha1 subunit. Epilepsia. 2012;53:e161–5. [PMC free article] [PubMed] [Google Scholar]

3. Binder DK, Oshio K, Ma T, Verkman AS, Manley GT. Increased seizure threshold in mice lacking aquaporin-4 water channels. Neuroreport. 2004;15:259–62. [PubMed] [Google Scholar]

4. Chung WK, Shin M, Jaramillo TC, Leibel RL, LeDuc CA, Fischer SG, Tzilianos E, Gheith AA, Lewis AS, Chetkovich DM. Absence epilepsy in apathetic, a spontaneous mutant mouse lacking the h channel subunit, HCN2. Neurobiol Dis. 2009;33:499–508. [PMC free article] [PubMed] [Google Scholar]

5. Dong Y, Wang S, Zhang T, Zhao X, Liu X, Cao L, Chi Z. Ascorbic acid ameliorates seizures and brain damage in rats through inhibiting autophagy. Brain Res. 2013;1535:115–23. [PubMed] [Google Scholar]

6. Friedman D, Honig LS, Scarmeas N. Seizures and epilepsy in Alzheimer's disease. CNS neuroscience & therapeutics. 2012;18:285–94. [PMC free article] [PubMed] [Google Scholar]

7. Gonzalez-Ramirez M, Razo-Juarez LI, Sauer-Ramirez JL, Gonzalez-Trujano ME, Salgado-Ceballos H, Orozco-Suarez S. Anticonvulsive effect of vitamin C on pentylenetetrazol-induced seizures in immature rats. Pharmacol Biochem Behav. 2010;97:267–72. [PubMed] [Google Scholar]

8. Harrison FE, Yu SS, Van Den Bossche KL, Li L, May JM, McDonald MP. Elevated oxidative stress and sensorimotor deficits but normal cognition in mice that cannot synthesize ascorbic acid. J Neurochem. 2008;106:1198–1208. [PMC free article] [PubMed] [Google Scholar]

9. Harrison FE, May JM, McDonald MP. Vitamin C deficiency increases basal exploratory activity but decreases scopolamine-induced activity in APP/PSEN1 transgenic mice. Pharmacol Biochem Behav. 2010;94:543–52. [PMC free article] [PubMed] [Google Scholar]

10. Harrison FE. A critical review of vitamin C for the prevention of age-related cognitive decline and Alzheimer's disease. Journal of Alzheimer's disease : JAD. 2012;29:711–26. [PMC free article] [PubMed] [Google Scholar]

11. Minkeviciene R, Ihalainen J, Malm T, Matilainen O, Keksa-Goldsteine V, Goldsteins G, Iivonen H, Leguit N, Glennon J, Koistinaho J, Banerjee P, Tanila H. Age-related decrease in stimulated glutamate release and vesicular glutamate transporters in APP/PS1 transgenic and wild-type mice. J Neurochem. 2008;105:584–94. [PubMed] [Google Scholar]

12. Naseer MI, Ullah I, Ullah N, Lee HY, Cheon EW, Chung J, Kim MO. Neuroprotective effect of vitamin C against PTZ induced apoptotic neurodegeneration in adult rat brain. Pakistan journal of pharmaceutical sciences. 2011;24:263–8. [PubMed] [Google Scholar]

13. Pandis D, Scarmeas N. Seizures in Alzheimer disease: clinical and epidemiological data. Epilepsy currents / American Epilepsy Society. 2012;12:184–7. [PMC free article] [PubMed] [Google Scholar]

14. Proper EA, Hoogland G, Kappen SM, Jansen GH, Rensen MG, Schrama LH, van Veelen CW, van Rijen PC, van Nieuwenhuizen O, Gispen WH, de Graan PN. Distribution of glutamate transporters in the hippocampus of patients with pharmaco-resistant temporal lobe epilepsy. Brain : a journal of neurology. 2002;125:32–43. [PubMed] [Google Scholar]

15. Rauca C, Zerbe R, Jantze H. Formation of free hydroxyl radicals after pentylenetetrazol-induced seizure and kindling. Brain Res. 1999;847:347–51. [PubMed] [Google Scholar]

16. Santos IM, da Tome AR, Saldanha GB, Ferreira PM, Militao GC, Freitas RM. Oxidative stress in the hippocampus during experimental seizures can be ameliorated with the antioxidant ascorbic acid. Oxidative medicine and cellular longevity. 2009;2:214–21. [PMC free article] [PubMed] [Google Scholar]

17. Snead OC, 3rd, Depaulis A, Vergnes M, Marescaux C. Absence epilepsy: advances in experimental animal models. Advances in neurology. 1999;79:253–78. [PubMed] [Google Scholar]

18. Sotiriou S, Gispert S, Cheng J, Wang Y, Chen A, Hoogstraten-Miller S, Miller GF, Kwon O, Levine M, Guttentag SH, Nussbaum RL. Ascorbic-acid transporter Slc23a1 is essential for vitamin C transport into the brain and for perinatal survival. Nat Med. 2002;8:514–7. [PubMed] [Google Scholar]

19. Vossel KA, Beagle AJ, Rabinovici GD, Shu H, Lee SE, Naasan G, Hegde M, Cornes SB, Henry ML, Nelson AB, Seeley WW, Geschwind MD, Gorno-Tempini ML, Shih T, Kirsch HE, Garcia PA, Miller BL, Mucke L. Seizures and epileptiform activity in the early stages of Alzheimer disease. JAMA neurology. 2013;70:1158–66. [PMC free article] [PubMed] [Google Scholar]

20. Xavier SM, Barbosa CO, Barros DO, Silva RF, Oliveira AA, Freitas RM. Vitamin C antioxidant effects in hippocampus of adult Wistar rats after seizures and status epilepticus induced by pilocarpine. Neurosci Lett. 2007;420:76–9. [PubMed] [Google Scholar]

Vitamin C For Epilepsy

Source: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4306812/

Share:

What Is Considered High Dose Of Vitamin C

What Is Considered High Dose Of Vitamin C

  • Research
  • Open Access
  • Published:

Pilot trial of high-dose vitamin C in critically ill COVID-19 patients

  • Xin Rao1,6  na1,
  • Yiming Li1,6  na1,
  • Yuan Zhu1,
  • Fang Liu1,
  • Guangling Guo2,
  • Guoshi Luo3,
  • Zhongji Meng4,
  • Daniel De Backer5,
  • Hui Xiang1,6 &
  • Zhiyong Peng ORCID: orcid.org/0000-0002-3873-9607 1,6

Annals of Intensive Care volume 11, Article number:5 (2021) Cite this article

  • 48k Accesses

  • 39 Citations

  • 122 Altmetric

  • Metrics details

Abstract

Background

Few specific medications have been proven effective for the treatment of patients with severe coronavirus disease 2019 (COVID-19). Here, we tested whether high-dose vitamin C infusion was effective for severe COVID-19.

Methods

This randomized, controlled, clinical trial was performed at 3 hospitals in Hubei, China. Patients with confirmed severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infection in the ICU were randomly assigned in as 1:1 ratio to either the high-dose intravenous vitamin C (HDIVC) or the placebo. HDIVC group received 12 g of vitamin C/50 ml every 12 h for 7 days at a rate of 12 ml/hour, and the placebo group received bacteriostatic water for injection in the same way within 48 h of arrival to ICU. The primary outcome was invasive mechanical ventilation-free days in 28 days (IMVFD28). Secondary outcomes were 28-day mortality, organ failure (Sequential Organ Failure Assessment (SOFA) score), and inflammation progression (interleukin-6).

Results

Only 56 critical COVID-19 patients were ultimately recruited due to the early control of the outbreak. There was no difference in IMVFD28 between two groups (26.0 [9.0–28.0] in HDIVC vs 22.0 [8.50–28.0] in control, p = 0.57). HDIVC failed to reduce 28-day mortality (P = 0.27). During the 7-day treatment period, patients in the HDIVC group had a steady rise in the PaO2/FiO2 (day 7: 229 vs. 151 mmHg, 95% CI 33 to 122, P = 0.01), which was not observed in the control group. IL-6 in the HDIVC group was lower than that in the control group (19.42 vs. 158.00; 95% CI -301.72 to -29.79; P = 0.04) on day 7.

Conclusion

This pilot trial showed that HDIVC failed to improve IMVFD28, but might show a potential signal of benefit in oxygenation for critically ill patients with COVID-19 improving PaO2/FiO2 even though.

Introduction

Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infection has become a global health issue [1, 2]. While the majority of patients presented with mild symptoms and did not even need hospitalization [3], nearly 30% of adult patients suffer from severe pneumonia and acute respiratory distress syndrome (ARDS), often associated with sepsis or septic shock, and multiple organ (kidney, liver, and heart) failure. Patients with ARDS and systemic complications require critical care and lead to a higher risk of death [4, 5, 6]. Due to the lack of effective medications against SARS-COV-2, the main management is supportive therapy.

Similar to the pathophysiology of severe acute respiratory syndrome (SARS)-related ARDS, SARS-CoV-2 infection stimulates the innate immune system, causing numerous types of cytokine release, namely, a "cytokine storm", inducing systemic inflammatory response [7, 8] and multiple organ failure [9, 10]. A retrospective study on SARS suggested that the worsening after 2 weeks was not related to uncontrolled viral replication, but related to immunopathological damage [11]. Therefore, antiviral therapy alone may be insufficient to treat COVID-19 patients.

Vitamin C (ascorbic acid, ascorbate) functions as a potent water-soluble antioxidant by directly scavenging oxygen free radicals and acting as an essential co-factor for the production of catecholamines, vasopressin, and cortisol in the human body [12]. Vitamin C is also found in high concentrations in leukocytes and implicated in several immune responses and functions [13]. Emerging evidence in preclinical studies indicated that vitamin C played a crucial role in ameliorating the effects of inflammation by inhibiting proinflammatory cytokine production, assisting immunoregulation, neutralizing reactive oxygen species (ROS), and protecting host cells [14, 15]. Hypovitaminosis C was ubiquitous in critically ill patients, and approximately 40% of the patients had a severe deficiency [16], while the low vitamin C serum level cannot be corrected by oral supplementation due to the issue of pharmacokinetics [17]. In a latest research, of 18 adult ICU patients COVID-19 who met ARDS criteria, 94.4% had undetectable vitamin C levels and 1 patient had low levels [18]. Thus, high-dose intravenous vitamin C (HDIVC) was added to the standard therapy of critically ill patients in recent studies, such as sepsis [19,20,21], ARDS [21, 22], cardiac surgery [23], and burn [24]. The results showed that HDIVC was safe for critically ill patients and significantly reduced vasopressor support [25], limited organ injury [26], shortened the duration of mechanical ventilation [27] and ICU stay [28], and safety/feasibility in severe sepsis [19]. Additionally, vitamin C has direct nonspecific antiviral activity in vitro [29], although it is unclear whether this confers any protection to humans with COVID-19.

Therefore, we hypothesized that HDIVC together with conventional treatments would improve the outcomes for adult patients admitted to the ICU due to severe COVID-19 by preventing cytokine storms and reducing lung and other organ injuries. In this context, we conducted this multicenter, randomized, blind clinical trial to provide a therapeutic strategy for critically ill patients with COVID-19.

Methods

This study is a multicenter, randomized trial that was approved by the ethics committee of Zhongnan Hospital of Wuhan University (#2020001). This study was conducted in the ICUs of Zhongnan Hospital of Wuhan University, Leishenshan (Thunder God Mountain) Hospital, and Taihe Hospital from February 14, 2020, to March 29, 2020. The ICUs specifically for COVID-19 from Zhongnan Hospital and Leishenshan Hospital were managed by the same team. The trial was registered on the website of ClinicalTrials.gov (ID: NCT04264533; registered February 14 2020) before patient recruitment.

Patient enrollment

Patients were screened and enrolled following admission to the three ICUs. The patients who were diagnosed as severe SARS-CoV-2-related pneumonia, appeared or had a high risk of multiple organs injury would be transferred to ICU. The following inclusion criteria were met: (1) age  ≥ 18 and < 80 years; (2) RT-PCR positive for SARS-CoV-2; (3) pneumonia confirmed by chest imaging and admission to the ICU; (3) PaO2/FiO2(P/F) < 300 mmHg. Exclusion criteria were allergy to vitamin C, pregnancy or breastfeeding, expected survival duration < 24 h, and previous history of glucose-6-phosphate dehydrogenase deficiency or end-stage pulmonary disease. Patients who were already enrolled in other clinical trials were excluded as well. If these criteria were met within 48 h of ICU admission, informed consent was obtained from the patients or their family members. The reason was because the efficacies of the treatments could not be evaluated with limited times of treatment.

Randomization, allocation and blinding

Each ICU was assigned with an independent random numeric table generated by Microsoft Excel 2019 by the primary investigator alone. Each table had equal numbers of 1 and 2, which represented the placebo group (bacteriostatic water infusion) and treatment group (HDIVC), respectively. The generated random list was stored by the principal investigator who was not involved in the treatment of patients and hidden to the other investigators. When a patient was transferred to the ICU and met the enrollment criteria, the clinician on duty would inform the principal investigator and obtain a number from the list. Then, participants were enrolled in the corresponding group according to the chronological order of ICU recruitment. The grouping and intervention were unknown to the participants and investigators who were responsible for data collection and statistical analysis. VC injection and sterile water for injection were both colorless and contained in the same brown syringes with different marks and without explanations on the syringe to make sure that patients could not distinguish the treatment they receive.

Study interventions

Patients were randomized to receive vitamin C or placebo within 48 h after admission to the ICU. To control the infusion rates accurately and not affect the fluid management of severe patients, we infused vitamin C or placebo via central vein catheterization controlled by a pump. The study groups in this trial were (1) HDIVC: 24 g vitamin C per day. Patients were infused with 12 g vitamin C diluted in 50 ml of bacteriostatic water every 12 h at a rate of 12 ml/hour by infusion pump for 7 days. (2) Placebo: 50 ml of bacteriostatic water infused every 12 h at the same rate. Study interventions were initiated on the same day as informed consent and randomization. The preparation, transportation, storage, and use of therapies (VC and bacteriostatic water for injection) were in line with the drug management protocol in each hospital.

General treatments and standard procedure of ventilation supports

In addition, other general treatments followed the latest COVID-19 guidelines [30]. Oseltamivir and azithromycin were usually used in the general ward. After ICU admission, low weight molecular heparin was applied for the prevention deep vein thrombus. Piperacillin/tazobactam was used for patients receiving tracheal intubation.

If the patients showed the symptoms of rapid deterioration of hypoxemia, severe ARDS, or septic shock, hydrocortisone (1 mg/kg/day) could be considered.

Respiratory support (IMV, NIV and HFNC) were given to patients with hypoxic respiratory failure and ARDS. If respiratory failure could not be improved or worsened continuously within a short time after using HFNC or NIV, intubation were performed and the approach of lung-protective ventilation was applied. ECMO was considered as the rescue therapy when the refractory hypoxemia was difficult to be corrected by protective lung ventilation [4]. When patients' respiratory functions improved and were ready for weaning from the ventilators, the spontaneous breathing test (SBT) was performed. After the SBT was passed, invasive ventilator was considered to remove with the endotracheal tube extubation.

Risks and adverse events

Adverse events (AEs) related to HDIVC included (1) nausea or vomiting during or after infusion of VC; (2) electrolyte disturbance; and (3) acute kidney injury, as described by Khoshnam-Rad [31]. AEs and serious adverse events (SAEs) were observed and followed in accordance with the good clinical practice guidelines issued by the National Medical Products Administration of the People's Republic of China. If any severe adverse events were observed during infusion, the infusion was stopped immediately, and the patient's vital signs were carefully monitored. All the AEs and SAEs were recorded in detail, and the causal relationship between the infusion and AEs was analyzed.

Data collection and management

Baseline data, which included demographics, anthropometrics, comorbid conditions, vital signs, Acute Physiology and Chronic Health Evaluation II (APACHE II) scores, and Glasgow Coma Scale (GCS) scores, were obtained on the day of randomization. Laboratory data, Sequential Organ Failure Assessment (SOFA) scores, PaO2/FiO2, and other treatments used were monitored on days 1, 3, and 7 (day 1 was defined as the day of the first administration of study drug).

The primary outcome of the study was invasive mechanical ventilation (IMV)-free days in 28 days (IMVFD28). Secondary outcomes included 28-day mortality, organ functions and inflammatory parameters, including white blood cell counts, neutrophil counts, lymphocyte counts, procalcitonin, interleukin-6 (IL-6), and C-reactive protein (CRP). Multi-organ dysfunction was assessed using SOFA scores. Additionally, vasopressor days, respiratory support days (including invasive and noninvasive mechanical ventilation), IMVFD28, patient condition improvement rate, patient condition deterioration rate, length of ICU and hospital stay, ICU and in-hospital mortality were recorded as additional secondary outcomes of this research. IMVFD28s were defined as the number of days a patient was extubated after recruitment to day 28. If the patient died with MV, a value of zero was assigned. Deterioration of the patient's condition was defined as the patient requiring HFNC or NIV on day 1 and requiring ECMO or IMV, or dying, after 7 days of treatment. Improvement of the patient's condition was defined as the patient requiring ECMO or IMV on day 1 and switching to HFNC, NIV, or discharged from the ICU after 7 days of treatment. The P/F was calculated based on the PaO2/FiO2, and we choose the lowest values recorded on the specific day. All the data were collected from the clinical information system of three ICUs. Septic shock was identified according to International Guidelines for Management of Sepsis and Septic Shock (2016). Acute kidney injury was identified according to the Kidney Disease: Improving Global Outcomes definition. Acute cardiac injury was defined as the serum levels of troponin I were above the 99th percentile upper reference limit or new abnormalities were shown in electrocardiography and echocardiography. Acute liver failure (ALF), which is defined as coagulopathy (INR ≥ 1.5), hepatic encephalopathy, and onset less than 26 weeks in a patient without underlying chronic liver disease. Coagulation disorders were defined as the presence of D-dimer > 0.24 mg/L or FDP > 5 mg/L.

Statistical analysis

The sample size was calculated according to primary endpoint, as this trial began at the early stage of COVID-19, such preliminary data lacked, and the sample size was finally calculated from the previous studies on ARDS [21]. We used the non-inferiority test formula to calculate the sample size with a one-sided error rate (α) of 2.5%, a power of 80%, and a withdrawal rate of 10%, and the anticipated sample size was 140. With the control of the epidemic, this trial was stopped early, and the number of qualifying COVID-19 patients did not satisfy the anticipated sample size. Thus, we considered this trial as the pilot trial. Numerical variables are described as the mean with standard deviation (SD) or median with interquartile range (IQR) according to distribution and were compared with the t-test/Mann–Whitney U test. Category data are represented as frequencies and proportions and compared with the Chi-square test and Fisher's exact test. The primary intention-to-treat analysis included all randomized participants. For the outcome variables, the hazard ratio and 95% CI were estimated by the Cox proportional risk model for mortality, and odds ratios with 95% CI were calculated by binary logistic regression for the other variables. Kaplan–Meier analysis was used to estimate the 28-day mortality to reflect the early survival differences for the two groups, and survival curves were compared with the Wilcoxon test. Survival analyses were further performed in subgroup with SOFA score more than 2. The testing was 2-sided, and a P-value < 0.05 was considered statistically significant. SPSS 20.0 and GraphPad Prism 8.0 were used to complete data processing and statistical analysis.

Results

Baseline characteristics of the patients

A total of 66 patients were identified (Fig. 1), 56 patients of them were enrolled and randomized in this study from February 14, 2020, to March 29, 2020. Patients were enrolled in the Leishenshan (Thunder God Mountain) Hospital (39 patients), Zhongnan Hospital of Wuhan University (11 patients), and Taihe Hospital of Hubei University of Medicine (6 patients). All participants (56) were included in the primary intention-to-treat analysis, 50 (89.2%) received the full 7-day treatment course, 4 (7.14%) only received 5 or 6 days of treatment due to discharge from the ICU, and 2 of them only received treatment for less than 3 days due to early death of natural process. Tables 1 and 2 shows the baseline demographic and clinical characteristics of the 56 patients.

Fig. 1
figure1

Flowchart of patients. HDIVC high-dose intravenous vitamin C

Full size image

Table 1 Baseline characteristics of intention-to-treat patients

Full size table

Table 2 Outcomes in a trial of HDIVC in patients with COVID-19

Full size table

The average age of the study patients was 66.7 ± 12.7 years, and 66.1% of the patients were male. The APACHE II score of all patients was 13.5 (IQR, 10.2-15.7), with no differences between groups. The most common comorbidity was hypertension (44%), followed by diabetes (30%) and coronary heart disease (22%). The average time from symptom onset to starting HDIVC treatment was 17 (11–25) days. No significant differences in vital signs, laboratory results, disease severity, or treatments were observed between groups at baseline.

Primary outcome

The IMVFD28 was 26.0 days [9.0–28.0] in HDIVC, and 22.0 days [8.50–28.0] in placebo group, but this difference was not statistically significant (P = 0.57, HR, CI: 4.8[-4.7 to 7.2]) (Fig. 2). The post hoc computation of power for IMVFD28 was 0.3.

Fig. 2
figure2

The IMVFD28 in high-dose intravenous vitamin C and placebo group. The IMVFD28 was 26.0 days[9.0–28.0] in HDIVC, and 22.0 days[8.5–28.0] in placebo group, but this difference was not statistically significant (P = 0.57, CI 4.8[-4.7 to 7.2]). IMV invasive mechanical ventilation, HDIVC high-dose intravenous vitamin C

Full size image

Secondary outcomes

Kaplan–Meier analysis was used to estimate the 28-day mortality, and survival curves were compared with the Wilcoxon test (P = 0.27) among all the enrolled patients with COVID-19. Meanwhile, the Cox regression was used for comparisons (P = 0.31, HR, 0.50 [95% CI 0.2 to 1.8]). HDIVC infusion exhibited a trend of reduction in 28-day mortality (P = 0.06) in more severe patients (SOFA score ≥ 3) using univariate survival analysis, and Cox regression showed a similar results (P = 0.07, HR, 0.32 [95% CI 0.10–1.06]) (Fig. 3).

Fig. 3
figure3

The 28-day mortality from randomization (day 1) to day 28. a Kaplan–Meier analysis was used to estimate the 28-day mortality, and survival curves were compared with the Wilcoxon test (P = 0.27) among patients with COVID-19. Cox regression was used for multiple comparisons (P = 0.31, HR, 0.50 [95% CI 0.2 to 1.8]). b Kaplan–Meier analysis was used to estimate the 28-day mortality and survival curves were compared with the Wilcoxon test (P = 0.06) among severe COVID-19 patients (baseline SOFA score ≥ 3). Cox regression was used as multiple comparisons (P = 0.07, HR, 0.32 [95% CI 0.10–1.06]). HDIVC high-dose intravenous vitamin C, COVID-19 coronavirus disease 2019, SOFA Sequential Organ Failure Assessment

Full size image

As shown in Fig. 4, the median SOFA score increased from 2.0 to 6.0 in the placebo group while it slightly decreased from 3.5 to 3.0 in the HDIVC group on day 7. However, there was no statistically significant difference in SOFA scores between the two groups on days 3 and 7. During the 7-day treatment period, the P/F in the HDIVC group was 228.5 mmHg, and 150.7 mmHg in the control group (95% CI 33.2 to 122.5; P = 0.01), and improved over time in HDIVC group (Fig. 4). The delta P/F from day 1 to day 7 was (20.0 ± 96.7 in HDVIC and. -51.9 ± 150.7 in control, P = 0.04 (difference 41.0 (5.9–172.5)). IL-6 in the HDIVC group dropped to 9.4 pg/ml, while it increased to 158.0 pg/ml in the placebo group (95% CI -301.7, -29.8; P = 0.04) on day 7. There was no significant difference in other anticipated infectious indicators and inflammation biomarkers between the two groups (Table 3). In addition, total bilirubin was 8.40 in HDIVC group, and 14.9 in placebo group (95% CI -18.3 to -0.6; P = 0.03, Table 3). The ICU mortality of severe patients (baseline SOFA score ≥ 3, n = 42) was improved in the HDIVC group (P = 0.03, HR, 0.22 [95% CI 0.1–0.9]).

Fig. 4
figure4

P/F and SOFA scores following high-dose intravenous vitamin C treatment. a The bars show the standard deviation (SD) of the mean. The P/F in both groups was approximately 200 at enrollment. After initiation of treatment, there was a steady rise in the P/F in the HDIVC group and a decline in the P/F in the placebo group (day 3: 217 vs. 189, 95% CI -34 to 90, P = 0.37; day 7: 229 vs. 151, 95% CI 33 to 122, P = 0.01). b 7 of P/F means the difference between the value from Day1 to Day7. Boxes represent the median and interquartile range (25th and 75th percentiles), and whiskers represent the range of values. The delta P/F ratio showed a different result in two groups (20.0 ± 96.68 vs. -51.88 ± 150.72, P = 0.04, 41.02 (5.92–172.45)). 7 was calculated by the difference between the value from Day 1 to Day 7. c The bars showed the interquartile range (IQR) of the median. There was no difference in the initial Sequential Organ Failure Assessment (SOFA) scores of the 2 groups at baseline (vitamin C vs placebo, median, 3.5[3.0–6.8] vs 2.0 [3.0–5.0]). After 7-day treatment, the median of SOFA score increased from 2.0 to 6.0 in the placebo group and slightly decreased from 3.5 to 3.0 in the HDIVC group, but there was no difference between the 2 groups. d 7 of SOFA scores means the difference between the value from Day1 to Day7. Boxes represent the median and interquartile range (25th and 75th percentiles), and whiskers represent the range of values. The delta SOFA scores showed no significant difference in two groups (0.0[-2.75-1.0] vs. 0.0[-1.0-3.5], P = 0.25, CI -1.35(-3.04-0.34)). 7 was calculated by the difference between the value from Day 1 to Day 7. HDIVC high-dose intravenous vitamin C, SOFA Sequential Organ Failure Assessment, P/F PaO2/FiO2 COVID-19 coronavirus disease 2019

Full size image

Table 3 Laboratory findings in a trial of HDIVC in patients with COVID-19

Full size table

The differences of other treatments

Table 1 demonstrates the differences in other treatments between the two groups. There were no significant differences in corticosteroids, antiviral agents or antibiotics.

Adverse events

During the 7-day infusion period, serum creatinine was 64.20[46.58–85.45] on day 1 and 57.50[39.95–71] umol/L on day 7 in HDIVC, versus 64.20[52.00 -81.70] on day 1 and 63.50[51.70–104.50] umol/L on day 7 in control group. Similarly, there were no changes in total bilirubin from day 1 to day 7 in HDIVC, while there was a slight increase from day 1 to day 7 in placebo. No other study-related adverse events were found, and no patients hadn't finished the study due to SAEs.

Discussion

This pilot trial shows that the addition of high-dose (24 g per day for 7 days) intravenous vitamin C to the standard-of-care treatment for severe COVID-19 did not affect ventilation-free days, but may provide a potential signal of benefit in oxygenation and IL-6. To our understanding, it was the first trial on a high dose of vitamin C infusion in patients with severe COVID-19.

Other previous studies suggested a protective role of vitamin C infusion in acute lung injury (ALI) and ARDS [21]. Moreover, the latest meta-analysis from eight vitamin C trials of a total of 685 patients indicated that vitamin C shortened the duration of mechanical ventilation in critically ill patients [27]. SARS-CoV-2 primarily affects the lung and causes pneumonia. Respiratory failure from ARDS is the leading cause of mortality from COVID-19 [32]. Similar to sepsis-induced ALI/ARDS, the rapid increase in cytokines in COVID-19 causes neutrophil sequestration in the lung, which damages the alveolar capillaries [9, 10]. In sepsis modeling of mice, parenterally infused VC demonstrated a protective effect on the lung [33, 34]. The potential mechanisms included limiting cytokine surges, improving alveolar fluid clearance, preventing vascular injury, restoring endothelial and alveolar epithelial integrity, and augmenting lung barrier cell function. In our study, the primary endpoint, mechanic ventilation-free days, was not demonstrated statistical significance due to the limited sample size, and late initiating HDIVC. However, the P/F increased, which was likely the result of pulmonary ventilation function improvement, based on the above mechanisms.

Previous clinical trials showed that HDIVC may reduce the extent of multiple organ failure and may improve the short-term outcomes of sepsis [19, 21], even though results in sepsis have been quite variable (ref Australian study/VICTAS just presented at ESICM). Additionally, plasma ascorbic acid levels were inversely correlated with the incidence of multiple organ failure and the risk of mortality [35]. We suspected that patients with worse organ dysfunction may have a more severe vitamin C deficiency, while high-dose intravenous VC effectively improved the deficiency and subsequently improved organ function [16]. Thus, the benefit was more significant in more severe COVID-19 patients with a higher baseline SOFA score in our study.

In this study, we chose 24 g of vitamin C infusion for 7 days. The main reason was based on two aspects: the efficacy and safety. The metabolism of vitamin C (VC) in the blood is very fast, only large dose and long course of VC supplement can maintain an adequate concentration in blood. In a previous study [19], 50 or 200 mg/kg/day (equivalent to 12 g/day) in 4 days VC treatment showed a signal of benefit in sepsis or ARDS patients. Similar daily doses were used in the Fowler paper (JAMA), which was associated with an improved outcome Thus, we tried to improve the efficacy by increasing the dosage and course in this trial. Actually, the 24 g dose is far less than the conventional IVC dose for cancer patients. In addition, high-dose VC has been clinically used for several decades and a recent NIH expert panel document states clearly that this regimen (1.5 g/kg body weight) is safe and without major adverse events (https://www.cancer.gov/about-cancer/treatment/cam/hp/vitamin-c-pdq). Therefore, we believe that this 24 g/day for 7 days is safe and more effective.

In addition, high levels of IL-6 were observed in patients with COVID-19 and might serve as a predictive biomarker for disease severity [5, 36, 37]. Mechanistically, IL-6 acts as a critical cytokine in the systemic inflammatory response [38], leading to a myriad of biological effects that contribute to pulmonary infiltration and organ damage [39, 40]. In a recent trial, tocilizumab [41], a recombinant humanized anti-human IL-6 receptor antibody, improved clinical symptoms by attenuating inflammation in COVID-19. The findings of the decline in IL-6 in our cohort were consistent with basic research showing that vitamin C inhibited the production and release of proinflammatory cytokines from human monocytes (IL-1, IL-2, IL-6, and TNF-α) [42]. Previous animal studies on SARS-CoV also demonstrated that inhibiting NF-κB, together with reduced IL-6 levels, could increase the survival rate in infected animals [37].

This study has several limitations. First, the study was started in the second half of the outbreak in China, and the number of qualifying COVID-19 patients decreased with the control of the epidemic so that we had to stop our trial before reaching the predefined sample size. Secondly, the initiation of vitamin C occurred more than 10 days after the first symptom, which may affect the efficacy of HDIVC. However, SARS-CoV-2 infection was characterized by mild symptoms initially, followed one week later by a rapid deterioration leading to hospitalization, and ARDS always occurred at the day 8 after the first symptom [4]. As in other randomized trial, administration of vitamin C was initiated shortly after the onset of ARDS [21], which started a couple of days earlier than our trial. Third, the absence of data on the monitoring of serum ascorbic acid concentration and assessment of viral load made it unclear whether vitamin C has direct antiviral activity against SARS-CoV-2. Fourth, we did not measure the anti-oxidative variables due to the complexity of the blood sample treatment, which was also an important feature for vitamin C. Finally, the imbalance in the patient gender distribution between the groups at baseline may have slightly influenced the outcomes.

Conclusion

In summary, this pilot trial showed that HDIVC did not improve the primary endpoint, IMVFD28, but demonstrated a potential signal of benefit for critically ill COVID-19, with an improvement in P/F ratio. Nevertheless, further large-scale RCTs are still needed to confirm our understanding of the effect of HDIVC therapy in critically ill patients with COVID-19.

Availability of data and materials

The datasets used and analyzed during the current study are available from the corresponding author on reasonable request.

References

  1. 1.

    Tian S, Hu W, Niu L, Liu H, Xu H, Xiao SY. Pulmonary pathology of early-phase 2019 novel coronavirus (COVID-19) pneumonia in two patients with lung cancer. J Thorac Oncol. 2020;15(5):700–4.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  2. 2.

    Munster VJ, Koopmans M, van Doremalen N, van Riel D, de Wit E. A novel coronavirus emerging in china - key questions for impact assessment. N Engl J Med. 2020;382(8):692–4.

    CAS  PubMed  Article  Google Scholar

  3. 3.

    Guan WJ, Ni ZY, Hu Y, Liang WH, Ou CQ, He JX, Liu L, Shan H, Lei CL, Hui DSC, et al. Clinical characteristics of coronavirus disease 2019 in China. N Engl J Med. 2020;382(18):1708–20.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  4. 4.

    Wang D, Hu B, Hu C, Zhu F, Liu X, Zhang J, Wang B, Xiang H, Cheng Z, Xiong Y et al: Clinical Characteristics of 138 Hospitalized Patients With 2019 Novel Coronavirus-Infected Pneumonia in Wuhan, China. JAMA 2020.

  5. 5.

    Zhou F, Yu T, Du R, Fan G, Liu Y, Liu Z, Xiang J, Wang Y, Song B, Gu X, et al. Clinical course and risk factors for mortality of adult inpatients with COVID-19 in Wuhan, China: a retrospective cohort study. Lancet. 2020;395(10229):1054–62.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  6. 6.

    Richardson S, Hirsch JS, Narasimhan M, Crawford JM, McGinn T, Davidson KW, Barnaby DP, Becker LB, Chelico JD, Cohen SL et al: Presenting Characteristics, Comorbidities, and Outcomes Among 5700 Patients Hospitalized With COVID-19 in the New York City Area. JAMA 2020.

  7. 7.

    Braciale TJ, Sun J, Kim TS. Regulating the adaptive immune response to respiratory virus infection. Nat Rev Immunol. 2012;12(4):295–305.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  8. 8.

    Chen G, Wu D, Guo W, Cao Y, Huang D, Wang H, Wang T, Zhang X, Chen H, Yu H, et al. Clinical and immunological features of severe and moderate coronavirus disease 2019. J Clin Investig. 2020;130(5):2620–9.

    CAS  PubMed  Article  Google Scholar

  9. 9.

    Xu Z, Shi L, Wang Y, Zhang J, Huang L, Zhang C, Liu S, Zhao P, Liu H, Zhu L, et al. Pathological findings of COVID-19 associated with acute respiratory distress syndrome. Lancet Respir Med. 2020;8(4):420–2.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  10. 10.

    Qin C, Zhou L, Hu Z, Zhang S, Yang S, Tao Y, Xie C, Ma K, Shang K, Wang W et al: Dysregulation of immune response in patients with COVID-19 in Wuhan, China. Clin Infect Dis 2020.

  11. 11.

    Peiris JS, Chu CM, Cheng VC, Chan KS, Hung IF, Poon LL, Law KI, Tang BS, Hon TY, Chan CS, et al. Clinical progression and viral load in a community outbreak of coronavirus-associated SARS pneumonia: a prospective study. Lancet. 2003;361(9371):1767–72.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  12. 12.

    Carr AC, Shaw GM, Fowler AA, Natarajan R. Ascorbate-dependent vasopressor synthesis: a rationale for vitamin C administration in severe sepsis and septic shock? Crit Care. 2015;19:418.

    PubMed  PubMed Central  Article  Google Scholar

  13. 13.

    Koekkoek WA, van Zanten AR. Antioxidant vitamins and trace elements in critical illness. Nutr Clin Pract. 2016;31(4):457–74.

    CAS  PubMed  Article  Google Scholar

  14. 14.

    Nieman DC, Peters EM, Henson DA, Nevines EI, Thompson MM. Influence of vitamin C supplementation on cytokine changes following an ultramarathon. J Interferon Cytokine Res. 2000;20(11):1029–35.

    CAS  PubMed  Article  Google Scholar

  15. 15.

    Vassilakopoulos T, Karatza MH, Katsaounou P, Kollintza A, Zakynthinos S, Roussos C: Antioxidants attenuate the plasma cytokine response to exercise in humans. J Appl Physiol (1985) 2003, 94(3):1025–1032.

  16. 16.

    Carr AC, Rosengrave PC, Bayer S, Chambers S, Mehrtens J, Shaw GM. Hypovitaminosis C and vitamin C deficiency in critically ill patients despite recommended enteral and parenteral intakes. Crit Care. 2017;21(1):300.

    PubMed  PubMed Central  Article  Google Scholar

  17. 17.

    Padayatty SJ, Sun H, Wang Y, Riordan HD, Hewitt SM, Katz A, Wesley RA, Levine M. Vitamin C pharmacokinetics: implications for oral and intravenous use. Ann Intern Med. 2004;140(7):533–7.

    CAS  PubMed  Article  Google Scholar

  18. 18.

    Chiscano-Camon L, Ruiz-Rodriguez JC, Ruiz-Sanmartin A, Roca O, Ferrer R. Vitamin C levels in patients with SARS-CoV-2-associated acute respiratory distress syndrome. Crit Care. 2020;24(1):522.

    PubMed  PubMed Central  Article  Google Scholar

  19. 19.

    Fowler AA, Syed AA, Knowlson S, Sculthorpe R, Farthing D, DeWilde C, Farthing CA, Larus TL, Martin E, Brophy DF, et al. Phase I safety trial of intravenous ascorbic acid in patients with severe sepsis. J Transl Med. 2014;12:32.

    PubMed  PubMed Central  Article  CAS  Google Scholar

  20. 20.

    Fujii T, Luethi N, Young PJ, Frei DR, Eastwood GM, French CJ, Deane AM, Shehabi Y, Hajjar LA, Oliveira G et al: Effect of Vitamin C, Hydrocortisone, and Thiamine vs Hydrocortisone Alone on Time Alive and Free of Vasopressor Support Among Patients With Septic Shock: The VITAMINS Randomized Clinical Trial. JAMA 2020.

  21. 21.

    Fowler AA, Truwit JD, Hite RD, Morris PE, DeWilde C, Priday A, Fisher B, Thacker LR, Natarajan R, Brophy DF, et al. Effect of vitamin C infusion on organ failure and biomarkers of inflammation and vascular injury in patients with sepsis and severe acute respiratory failure: the CITRIS-ALI randomized clinical trial. JAMA. 2019;322(13):1261–70.

    PubMed  PubMed Central  Article  Google Scholar

  22. 22.

    Fowler Iii AA, Kim C, Lepler L, Malhotra R, Debesa O, Natarajan R, Fisher BJ, Syed A, DeWilde C, Priday A, et al. Intravenous vitamin C as adjunctive therapy for enterovirus/rhinovirus induced acute respiratory distress syndrome. World J Crit Care Med. 2017;6(1):85–90.

    PubMed  PubMed Central  Article  Google Scholar

  23. 23.

    Hu X, Yuan L, Wang H, Li C, Cai J, Hu Y, Ma C. Efficacy and safety of vitamin C for atrial fibrillation after cardiac surgery: A meta-analysis with trial sequential analysis of randomized controlled trials. Int J Surg. 2017;37:58–64.

    PubMed  Article  Google Scholar

  24. 24.

    Tanaka H, Matsuda T, Miyagantani Y, Yukioka T, Matsuda H, Shimazaki S. Reduction of resuscitation fluid volumes in severely burned patients using ascorbic acid administration: a randomized, prospective study. Arch Surg. 2000;135(3):326–31.

    CAS  PubMed  Article  Google Scholar

  25. 25.

    Li J. Evidence is stronger than you think: a meta-analysis of vitamin C use in patients with sepsis. Crit Care. 2018;22(1):258.

    PubMed  PubMed Central  Article  Google Scholar

  26. 26.

    Xu Y, Zheng X, Liang B, Gao J, Gu Z. Vitamins for prevention of contrast-induced acute kidney injury: a systematic review and trial sequential analysis. Am J Cardiovasc Drugs. 2018;18(5):373–86.

    CAS  PubMed  Article  Google Scholar

  27. 27.

    Hemila H, Chalker E. Vitamin C may reduce the duration of mechanical ventilation in critically ill patients: a meta-regression analysis. J Intensive Care. 2020;8:15.

    PubMed  PubMed Central  Article  Google Scholar

  28. 28.

    Hemila H, Chalker E: Vitamin C Can Shorten the Length of Stay in the ICU: A Meta-Analysis. Nutrients 2019, 11(4).

  29. 29.

    Madhusudana SN, Shamsundar R, Seetharaman S. In vitro inactivation of the rabies virus by ascorbic acid. Int J Infect Dis. 2004;8(1):21–5.

    CAS  PubMed  Article  Google Scholar

  30. 30.

    Jin YH, Cai L, Cheng ZS, Cheng H, Deng T, Fan YP, Fang C, Huang D, Huang LQ, Huang Q, et al. A rapid advice guideline for the diagnosis and treatment of 2019 novel coronavirus (2019-nCoV) infected pneumonia (standard version). Mil Med Res. 2020;7(1):4.

    CAS  PubMed  PubMed Central  Google Scholar

  31. 31.

    Khoshnam-Rad N, Khalili H. Safety of vitamin C in sepsis: a neglected topic. Curr Opin Crit Care. 2019;25(4):329–33.

    PubMed  Article  Google Scholar

  32. 32.

    Ruan Q, Yang K, Wang W, Jiang L, Song J. Clinical predictors of mortality due to COVID-19 based on an analysis of data of 150 patients from Wuhan. China Intensive Care Med. 2020;46(5):846–8.

    CAS  PubMed  Article  Google Scholar

  33. 33.

    Fisher BJ, Kraskauskas D, Martin EJ, Farkas D, Wegelin JA, Brophy D, Ward KR, Voelkel NF, Fowler AA 3rd, Natarajan R. Mechanisms of attenuation of abdominal sepsis induced acute lung injury by ascorbic acid. Am J Physiol Lung Cell Mol Physiol. 2012;303(1):L20-32.

    CAS  PubMed  Article  Google Scholar

  34. 34.

    Fisher BJ, Seropian IM, Kraskauskas D, Thakkar JN, Voelkel NF, Fowler AA 3rd, Natarajan R. Ascorbic acid attenuates lipopolysaccharide-induced acute lung injury. Crit Care Med. 2011;39(6):1454–60.

    CAS  PubMed  Article  Google Scholar

  35. 35.

    De Grooth HMS-dM, A.M.; Oudermans-van Straaten, H.M. : Early plasma vitamin C concentration, organ dysfunction and ICU mortality. Intensive Care Med 2014:40, S199.

  36. 36.

    Chen X, Zhao B, Qu Y, Chen Y, Xiong J, Feng Y, Men D, Huang Q, Liu Y, Yang B et al: Detectable serum SARS-CoV-2 viral load (RNAaemia) is closely correlated with drastically elevated interleukin 6 (IL-6) level in critically ill COVID-19 patients. Clinical infectious diseases : an official publication of the Infectious Diseases Society of America 2020.

  37. 37.

    Ruan Q, Yang K, Wang W, Jiang L, Song J. Clinical predictors of mortality due to COVID-19 based on an analysis of data of 150 patients from Wuhan China. Intensive Care Med. 2020;46(5):846–8.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  38. 38.

    Liu B, Li M, Zhou Z, Guan X, Xiang Y. Can we use interleukin-6 (IL-6) blockade for coronavirus disease (COVID-19)-induced cytokine release syndrome (CRS). J Autoimmun. 2020;111:102452.

    CAS  PubMed  PubMed Central  Article  Google Scholar

  39. 39.

    Tanaka T, Narazaki M, Kishimoto T. Immunotherapeutic implications of IL-6 blockade for cytokine storm. Immunotherapy. 2016;8(8):959–70.

    CAS  Article  PubMed  Google Scholar

  40. 40.

    Pathan N, Hemingway CA, Alizadeh AA, Stephens AC, Boldrick JC, Oragui EE, McCabe C, Welch SB, Whitney A, O'Gara P, et al. Role of interleukin 6 in myocardial dysfunction of meningococcal septic shock. Lancet. 2004;363(9404):203–9.

    CAS  Article  PubMed  Google Scholar

  41. 41.

    Xu X, Han M, Li T, Sun W, Wang D, Fu B, Zhou Y, Zheng X, Yang Y, Li X et al: Effective treatment of severe COVID-19 patients with tocilizumab. Proc Natl Acad Sci U S A 2020.

  42. 42.

    Hartel C, Strunk T, Bucsky P, Schultz C. Effects of vitamin C on intracytoplasmic cytokine production in human whole blood monocytes and lymphocytes. Cytokine. 2004;27(4–5):101–6.

    CAS  PubMed  Article  Google Scholar

Download references

Acknowledgements

Zhang, Xiang, and Peng had full access to all of the data in the study and take responsibility for the integrity of the data and the accuracy of the data analysis. Zhang, Rao and Li contributed equally and share first authorship. Xiang and Peng are the co-corresponding authors. This work was funded by the Science and Technology Department of Hubei Province (2020FCA024, 2020FCA020), and the Fundamental Research Funds for the Central Universities (2042020kfxg18, 2042020kfxg13).

Funding

This work was funded by the Science and Technology Department of Hubei Province (2020FCA024, 2020FCA020), and the Special Project for Significant New Drug Research and Development in the Major National Science and Technology Projects of China (2020ZX09201007).

Author information

Author notes

  1. Jing Zhang, Xin Rao and Yiming Li contributed equally to this work

Affiliations

  1. Dept. of Critical Care Medicine, Zhongnan Hospital of Wuhan University, Wuhan, 430071, Hubei, China

    Jing Zhang, Xin Rao, Yiming Li, Yuan Zhu, Fang Liu, Hui Xiang & Zhiyong Peng

  2. Anti-Aging Medical Center, Taihe Hospital, Huibei University of Medicine, Shiyan, 442000, Hubei, China

    Guangling Guo

  3. Department of Pulmonary and Critical Care Medicine, Taihe Hospital, Huibei University of Medicine, Shiyan, 442000, Hubei, China

    Guoshi Luo

  4. Department of Infectious Diseases, Taihe Hospital, Huibei University of Medicine, Shiyan, 442000, Hubei, China

    Zhongji Meng

  5. Department of Intensive Care, CHIREC Hospitals, Université Libre de Bruxelles, Brussels, Belgium

    Daniel De Backer

  6. Clinical Research Center of Hubei Critical Care Medicine, Wuhan, 430071, Hubei, China

    Jing Zhang, Xin Rao, Yiming Li, Hui Xiang & Zhiyong Peng

Contributions

Concept and design: JZ, XR, YL. Acquisition, analysis, or interpretation of data: JZ, XR, YL, HX, GG, GL, ZM. Drafting of the manuscript: JZ, XR, YL, DB, ZP. Critical revision of the manuscript for important intellectual content: JZ, XR, YL, DB, ZP. Statistical analysis: JZ, YZ, FL. Obtained funding: HX, ZP. Administrative, technical, or material support: HX, XR, ZP. Supervision: HX, DB, ZP. All authors read and approved the final manuscript.

Corresponding authors

Correspondence to Hui Xiang or Zhiyong Peng.

Ethics declarations

Ethics approval and consent to participate

This study is a multicenter, randomized trial, which was approved by the ethic committee of Zhongnan Hospital of Wuhan University (#2020001). It was registered on the website of ClinicalTrials.gov (ID: NCT04264533) before patient recruitment. Informed consents were obtained from the patients or family members.

Competing interests

The authors declare no competing interests.

Additional information

Publisher's Note

Springer Nature remains neutral with regard to jurisdictional claims in published maps and institutional affiliations.

About this article

Verify currency and authenticity via CrossMark

Cite this article

Zhang, J., Rao, X., Li, Y. et al. Pilot trial of high-dose vitamin C in critically ill COVID-19 patients. Ann. Intensive Care 11, 5 (2021). https://doi.org/10.1186/s13613-020-00792-3

Download citation

  • Received:

  • Accepted:

  • Published:

  • DOI : https://doi.org/10.1186/s13613-020-00792-3

Keywords

  • High-dose intravenous vitamin C
  • Coronavirus disease 2019
  • Severe acute respiratory syndrome coronavirus 2

What Is Considered High Dose Of Vitamin C

Source: https://annalsofintensivecare.springeropen.com/articles/10.1186/s13613-020-00792-3

Share:

Recent Posts

banner